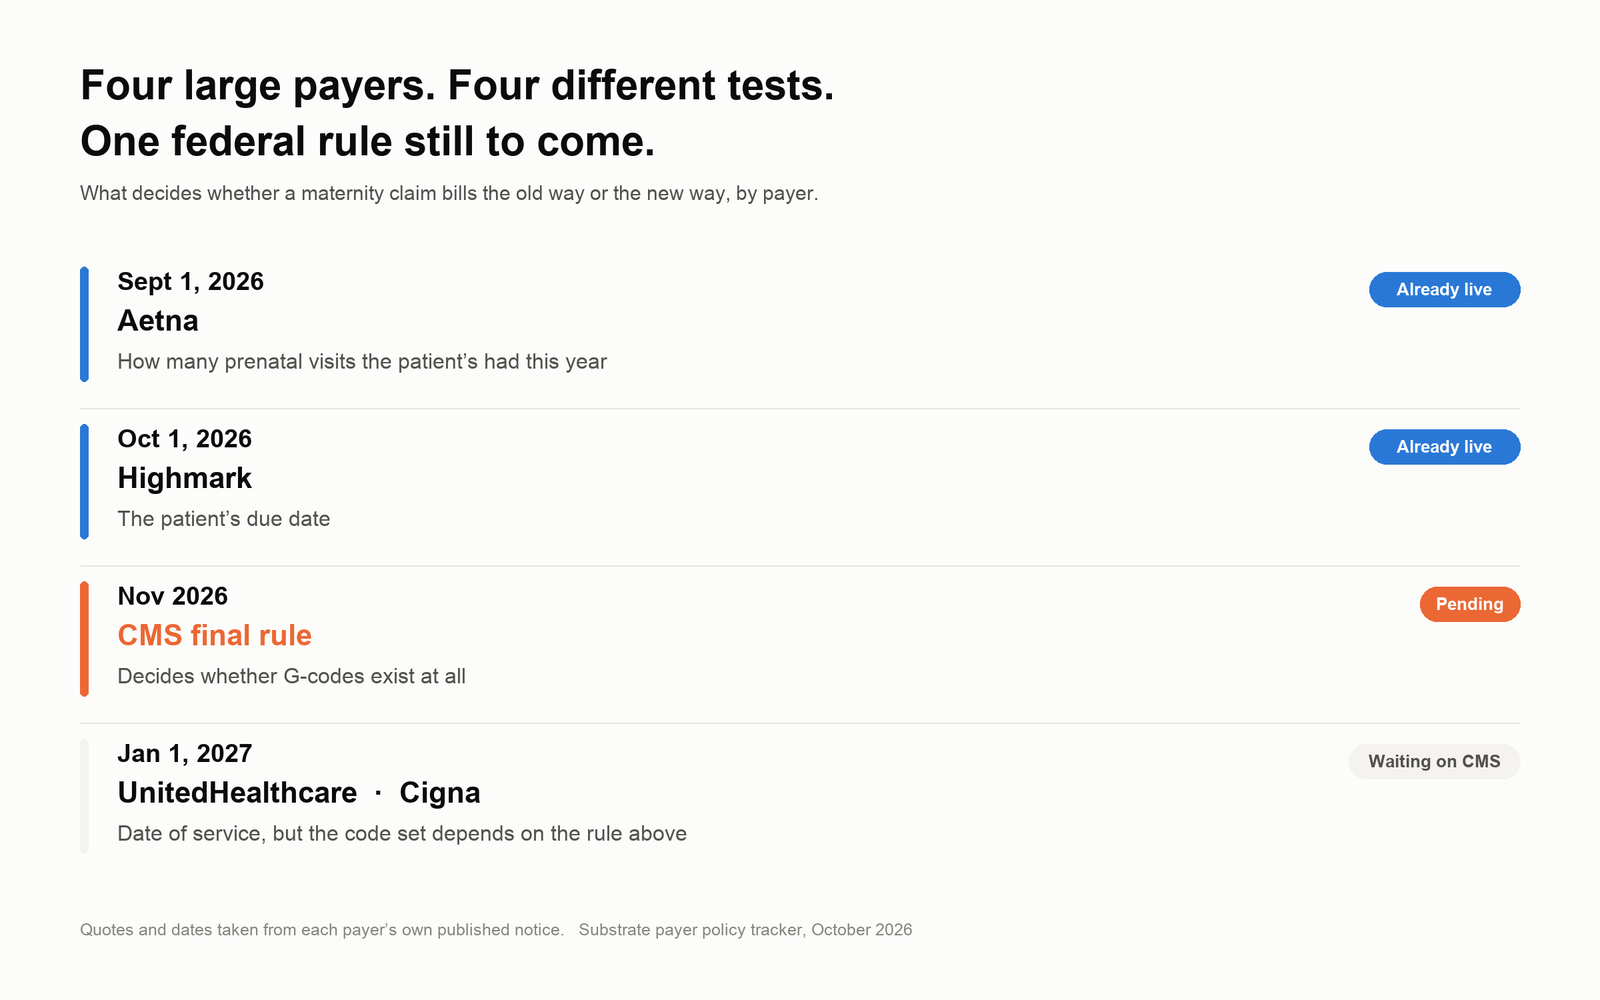




The conversation about the end of global OB billing is almost entirely about commercial payers.
Medicaid pays for roughly four in ten births nationally, and well over half at many safety-net hospitals. For a labor and delivery unit, it is frequently the single largest payer in the building.
It is also where we can see the least.
Nine states
We track over 3000 health plans. Across all 50 states and DC, nine have a confirmed 2027 maternity transition from a Medicaid-named plan:
- Illinois: Aetna Medicaid Illinois
- Maine: Maine Medicaid
- Massachusetts: Medicaid Massachusetts
- Michigan: AmeriHealth Caritas VIP Care
- New York: Medicaid New York, and Highmark BCBS Medicaid and CHP
- North Carolina: North Carolina Medicaid
- Ohio: Aetna OhioRISE Medicaid Managed Care
- Tennessee: Medicaid Tennessee, and BlueCare TennCare Select
- Washington: Medicaid Washington
In 40 states we have no Medicaid policy record at all.
Set that against the commercial side, where we have a confirmed transition from the state's Blue Cross Blue Shield licensee in 50 of 51 states. Commercial payers are responding far ahead of the state Medicaid plans so far.
Medicaid is harder to see
This is not because Medicaid programs are less organized. It is how they publish.
Bulletin archives, not policy pages. Medicaid guidance usually lands in a numbered bulletin, filed by date rather than by topic. A maternity billing change is often a single paragraph inside a bulletin covering six unrelated subjects, in a PDF named something like IM-2025-14.pdf. It's hard to search!
Managed care multiplies it. Several entries above are Medicaid managed care plans, not state programs. In a state with multiple MCOs, the state may publish one thing and each MCO may operationalize it differently, on its own timeline. Confirming a state means confirming the state program and every MCO under it.
The state and the MCO can disagree. Illinois and Ohio appear on that list through an MCO, not the state program. That is a confirmed transition for the plans those members are enrolled in, and it tells you nothing about the rest of the state's Medicaid population.
Why the gap costs more here
Volume. At roughly four in ten births nationally, a maternity billing change on the Medicaid side is not a corner case. For some units it is the main event.
Margin. Lower reimbursement per claim means rework eats a larger share of the payment. A denial that costs thirty dollars of staff time to fix is a very different proposition against a Medicaid delivery payment than a commercial one.
Small dollar denials get abandoned. The claims most likely to be written off unworked are exactly the ones Medicaid produces most of.
What to do if Medicaid is a meaningful share of your deliveries
Go to the bulletin archive, not the provider manual. Filter by date and read forward from early 2026. Do not search by keyword; the maternity item is usually inside a bulletin about something else.
Check each MCO separately. State guidance does not guarantee the managed care plans are aligned, or aligned on the same date. Your member mix determines which answer applies.
Ask in writing. Has the program published 2027 maternity billing guidance, where does it live, and what is the effective date. In writing, so it is forwardable to your coding team.
Treat an unconfirmed program as a live risk, not a quiet one. A program that has published nothing this close in is more likely to publish late and expect compliance quickly.
The list is live, and we enrich it daily
We track over 3000 health plans. 299 have a researched policy record so far: 181 confirmed, 57 proposed, and 61 describing current policy only. Proposed and current are never counted as a confirmed 2027 transition, which is why the Medicaid number is nine rather than something more flattering.
Every organization we could find that delivers babies has a public page listing its payers, what each has published, the effective date, and a link to the source. Free, no form, no sign-up. Someone works this list every day, and nine will not stay nine.
If your state Medicaid program has published 2027 maternity guidance, send us the bulletin number. It goes on the public list where every other provider in your state can use it.